
Quick answer
What Is Aortic Stenosis?
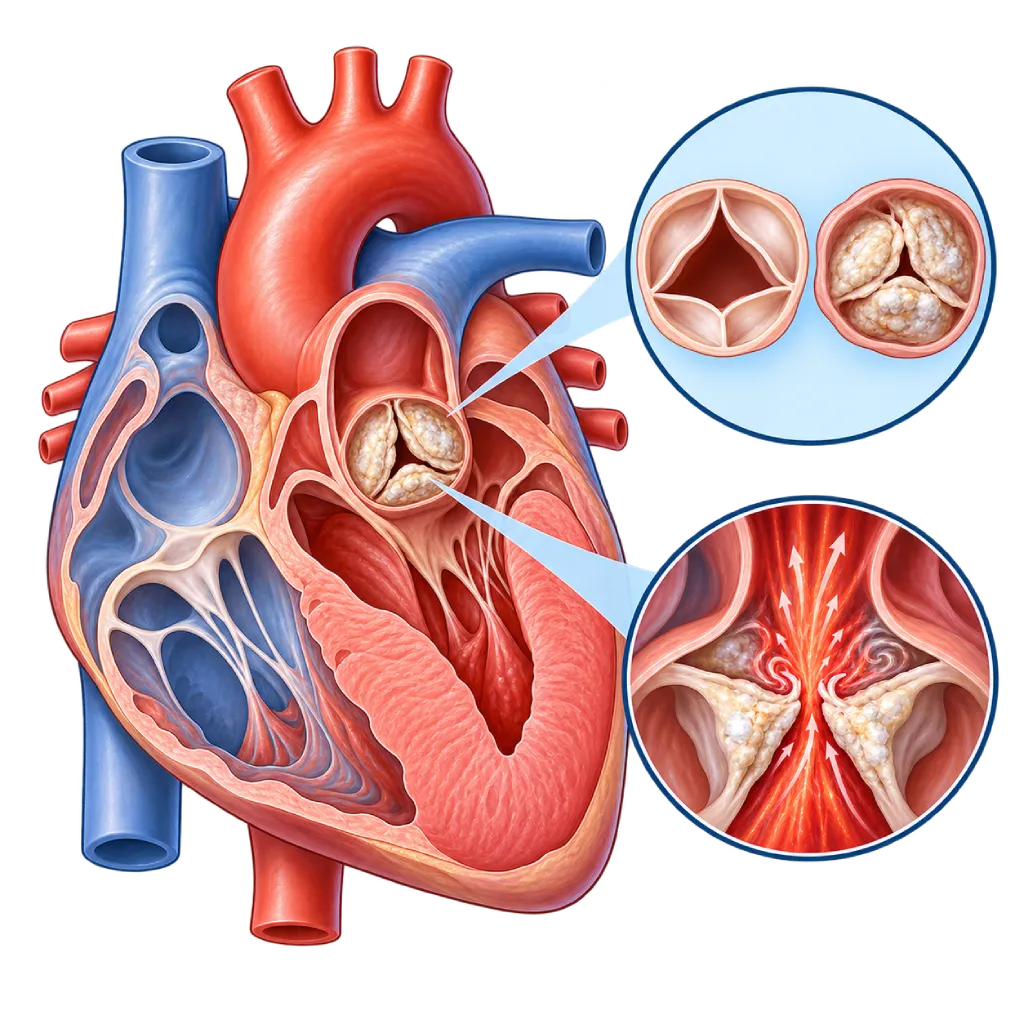
Aortic stenosis is a narrowing of the aortic valve, the doorway through which blood leaves the left ventricle for the rest of the body. A stiff valve makes the heart pump harder and, when severe, can cause shortness of breath, chest pain, or fainting.
SourcesSigns That Need Urgent Help
- Fainting, especially during or after activity
- Chest pain that does not go away with rest
- Severe shortness of breath at rest or waking at night short of breath
- Coughing up frothy or pink sputum with severe shortness of breath
- A very fast heartbeat with dizziness or weakness
If these signs appear, go to the nearest emergency department right away or call Heart Attack Center 1500 258.
01 / Understanding the condition
About Aortic Stenosis
The aortic valve sits between the left ventricle of the heart and the aorta, the body's main artery. Normally, this valve has three thin leaflets that open wide each time the heart pumps, then close so blood does not flow backward. In aortic stenosis, the valve leaflets become thick, stiff, and often calcified, so the opening gets smaller. Blood can still flow out, but the heart has to pump at a higher pressure. Aortic stenosis is one form of heart valve narrowing, covered on the Heart Valve Stenosis page.
How the Narrowing Develops
In older age, the main cause is wear and tear and calcium buildup over many years, similar to limescale building up. At younger ages, stenosis often develops in a bicuspid aortic valve, a valve present from birth that has only two leaflets, so it wears out and calcifies sooner. In regions where rheumatic fever is still common, valve damage from rheumatic heart disease is also a cause, and it usually comes with problems in the mitral valve.
Why It Often Goes Unnoticed at First
The muscle of the left ventricle adapts by thickening so it can still push blood through the narrow opening. That is why many people feel nothing for years. The condition is often discovered only when a doctor hears a heart murmur or during a heart ultrasound done for another reason. Symptoms usually appear once the narrowing is severe: shortness of breath or tiring quickly during activity, chest pain, and dizziness or fainting during activity.
Stages and Monitoring
Doctors classify aortic stenosis as mild, moderate, or severe based on the speed of blood flow through the valve, the pressure difference on either side of it, and the size of the valve opening. The narrowing usually progresses slowly, but the rate differs from person to person. That is why people with mild or moderate stenosis still need regular checkups and echocardiography even if they feel well.
Valve Replacement as the Main Treatment
There is no medication yet that can reopen a narrowed valve. Medications are used to control blood pressure, heart rhythm, or excess fluid. When the narrowing is severe and causing symptoms, or is starting to weaken the heart's pumping, the valve needs to be replaced, either through surgery or through a catheter. The choice is made together with the heart team based on your age, overall health, and the shape of your valve and blood vessels.
02 / Understanding the condition
Symptoms to Recognize.
Common Symptoms
- Often no symptoms, discovered from a heart murmur during an examination
- Shortness of breath or tiring quickly during activities that used to feel easy
- A gradual decline in the ability to walk long distances or climb stairs
- Pain, heaviness, or pressure in the chest during activity
- Dizziness or light-headedness during or after activity
- Heart palpitations
Symptoms in Older Adults
In older adults, symptoms are often vague because they are already less active, so they are easily considered a normal part of aging.
- Tiring easily, which is put down to aging
- Unknowingly cutting back on activity to avoid shortness of breath
- Unsteadiness, nearly fainting, or falling without a clear cause
- Shortness of breath when lying down that improves when sitting up
03 / Understanding the condition
What Causes This Condition?
- Calcium buildup and thickening of the aortic valve leaflets with age (degenerative aortic stenosis)
- A bicuspid aortic valve, a two-leaflet valve present from birth that wears out and calcifies sooner
- Valve damage from rheumatic fever in the past (rheumatic heart disease)
- Other congenital aortic valve abnormalities that are already narrow at birth, usually found in babies or children
- Rare causes, such as radiation therapy to the chest or advanced chronic kidney disease with calcium disorders
04 / Understanding the condition
Who Is at Higher Risk?
Age
The risk increases after age 65, because the wear and calcification of the valve develop over many years.
Genetic
A bicuspid aortic valve is present from birth and can be found in several members of a family, so stenosis can appear earlier, around age 50 to 70.
Medical
High blood pressure, high LDL cholesterol, high lipoprotein(a), diabetes, chronic kidney disease, and a history of rheumatic fever are linked to faster valve damage.
Lifestyle
Smoking and excess body weight are linked to valve calcification, although their effect is not as large as that of age.
Other
A history of radiation therapy to the chest, for example for lymphoma or breast cancer, can damage the valve years later.
Groups at Higher Risk
- Older Adults: Valve calcification increases with age, and symptoms in older adults are often vague because they are already less active.
- People with a Bicuspid Aortic Valve: A two-leaflet valve wears out sooner, so stenosis can appear several decades earlier and needs regular monitoring.
- Rheumatic Fever Survivors: Inflammation from rheumatic fever can slowly damage the aortic and mitral valves, often only noticeable years later.
- People with Chronic Kidney Disease: Imbalances of calcium and phosphate in advanced kidney disease speed up calcification of the heart valves.
- Cancer Survivors Who Had Chest Radiation: Radiation to the chest area can damage the heart valves years after treatment, so regular heart checkups are recommended.
05 / Understanding the condition
How Is It Diagnosed?
Aortic stenosis is often first suspected when a doctor hears a heart murmur with a stethoscope. From there, echocardiography is the main test to confirm the diagnosis. This heart ultrasound measures the speed of blood flow through the valve, the pressure difference, and the size of the valve opening, and assesses the thickness and strength of the left ventricle muscle.
If the results are unclear, for example when the heart's pumping is weak, your doctor may add a stress echocardiogram using medication or a CT scan to assess the amount of calcium on the valve. In severe stenosis that is not yet causing symptoms, an exercise test supervised by a doctor helps reveal hidden symptoms. The exercise test is not done if symptoms are already clear. Before valve replacement, a CT scan with contrast is used to measure the valve and the path through the blood vessels, while coronary angiography or coronary CT assesses the blood vessels of the heart.
Physical Examination
The doctor listens for the typical heart murmur at the upper right chest and checks your pulse and blood pressure.
Echocardiography
The main test: measures flow speed, pressure difference, valve opening area, and the thickness and strength of the left ventricle; repeated regularly for monitoring.
Electrocardiogram (ECG)
Looks for signs of thickening of the left ventricle muscle and rhythm disorders, such as atrial fibrillation or blocked electrical conduction in the heart.
Stress Echocardiography
Using a medication that stimulates the heart, it helps distinguish true severe stenosis from a valve that only looks narrow because the heart's pumping is weak.
Cardiac CT Scan
Measures the amount of calcium on the valve when the severity of stenosis is unclear, and maps the size of the valve and blood vessels before catheter-based valve implantation.
Treadmill Stress Test
Only for severe stenosis without symptoms: an exercise test supervised by a doctor helps reveal symptoms or an abnormal blood pressure response.
Coronary Angiography
Assesses narrowing of the coronary arteries before valve replacement, because the two are often found together in older age.
06 / Understanding the condition
Treatment Options.
Treatment is decided by a doctor after an assessment. The categories below can help you follow the conversation with your doctor.
Regular Monitoring
In mild to moderate stenosis, or severe stenosis without symptoms and with good heart pumping, your doctor schedules regular checkups and echocardiography according to how severe the narrowing is.
Medications for Coexisting Conditions
Medications do not open the narrowed valve, but they are used to control blood pressure, excess fluid, heart rhythm, and cholesterol. The type and dose are determined by your doctor.
Surgical Aortic Valve Replacement
The old valve is removed and replaced with a mechanical or biological artificial valve, through open-heart surgery or a small incision. It can be combined with coronary bypass surgery if needed.
Transcatheter Aortic Valve Implantation (TAVI)
A biological valve is inserted through a catheter, usually from an artery in the groin, then expanded inside the old valve without opening the chest. It is often chosen for older adults or people at high surgical risk.
Balloon Valvuloplasty
In adults, its effect is temporary, for example as a bridge to valve replacement. In babies and children with congenital stenosis, a balloon can be the initial treatment.
07 / Understanding the condition
Complications to Watch For.
Heart Failure
After working against a narrow valve for a long time, the left ventricle muscle can become stiff and then weaken, so fluid builds up in the lungs and legs. Covered on the Heart Failure page.
Fainting During Activity
During activity, blood flow through the narrow valve cannot increase enough, so blood flow to the brain drops briefly. Covered on the Syncope page.
Heart Rhythm Disorders
Atrial fibrillation and disorders of the heart's electrical conduction can develop; atrial fibrillation often makes symptoms worsen quickly.
Sudden Cardiac Arrest
The risk of sudden cardiac arrest increases once symptoms appear. In severe stenosis without symptoms the risk is low, but it is still a reason for regular checkups.
Gastrointestinal Bleeding
In some people, the strong flow through the valve damages one of the blood clotting proteins, leading to bleeding in the intestines and anemia.
Infective Endocarditis
A damaged valve is more easily infected by bacteria that enter the bloodstream. Covered on the Infective Endocarditis page.
08 / Understanding the condition
What Can You Do?
- Control your blood pressure, cholesterol, and blood sugar according to the targets set by your doctor.
- Quit smoking and maintain a healthy weight.
- Have children with a sore throat and fever checked so that bacterial infections are fully treated and rheumatic fever is prevented.
- Keep your teeth and mouth clean and have regular dental checkups to reduce the risk of valve infection.
- Have echocardiography on schedule if you are known to have a heart murmur or a bicuspid aortic valve.
- Ask your doctor what type and intensity of exercise is safe for the severity of your stenosis.
09 / Understanding the condition
When Should You See a Doctor?
See a cardiologist if you have been told you have a heart murmur or a bicuspid aortic valve, or if new symptoms appear during activity. If you already know you have stenosis, report any change in your symptoms, because such changes can be a sign that the valve needs to be replaced.
- Shortness of breath or tiring quickly during activities that used to feel easy
- Heaviness or pain in the chest when walking or climbing stairs
- Dizziness or nearly fainting during activity; if you actually faint, go to the emergency room right away
- Swollen legs or shortness of breath when lying down
- Plans for another surgery or a pregnancy while you are known to have aortic stenosis
Don't Wait in an Emergency.
If symptoms are severe or come on suddenly, go to the nearest emergency department right away or call Heart Attack Center 1500 258, rather than waiting for an appointment.
10 / Common questions
Questions You May Have.
Frequently asked questions about aortic stenosis.
Can aortic stenosis be cured with medication?
No medication has yet been proven to stop or reverse narrowing of the aortic valve. Medications are still useful for controlling blood pressure, excess fluid, heart rhythm, and cholesterol, which eases the strain on the heart. When the narrowing is severe and causing symptoms, or is starting to weaken the heart's pumping, the effective treatment is to replace the valve, through surgery or a catheter. Your doctor will explain the right timing based on your test results.
What is the difference between TAVI and aortic valve replacement surgery?
In surgery, the surgeon removes the old valve and sews in a mechanical or biological artificial valve, with the help of a heart-lung machine. In TAVI, a biological valve is folded onto the tip of a catheter, usually inserted through an artery in the groin, then expanded inside the old valve without opening the chest. The heart team weighs your age, surgical risk, the shape of your valve and blood vessels, and other conditions. TAVI is covered on the Transcatheter Aortic Valve Implantation (TAVI) page.
If I have no symptoms, do I still need checkups?
Yes. Aortic stenosis can get worse without you noticing, because many people unknowingly reduce their activity. Regular checkups and echocardiography help your doctor see changes in blood flow and pumping strength. Generally, tests are done every six months for severe stenosis, every year for moderate stenosis, and less often for mild stenosis. For some people with severe stenosis without symptoms, the doctor may suggest replacing the valve earlier.
Can people with aortic stenosis exercise?
Generally yes, but the type and intensity are adjusted to how severe the narrowing is. With mild stenosis, the majority of activities can be done. With moderate to severe stenosis, strenuous exercise, heavy lifting, and competitive sports usually need to be avoided. An exercise test supervised by a doctor can help determine safe limits. Stop the activity and get checked right away if you have chest pain, excessive shortness of breath, or dizziness during exercise.
How long can an artificial valve last?
A mechanical valve can last a very long time, but people who have one need a vitamin K antagonist blood thinner for life, with regular blood tests. A biological valve generally does not require long-term blood thinners, but it can wear out after about 10 to 20 years, sooner in younger people. If a biological valve wears out, it can sometimes be replaced again through a catheter. Your doctor helps choose the type of valve based on your age and life plans.
Does aortic stenosis run in families?
Aortic stenosis from calcification in older age is generally not directly inherited. However, a bicuspid aortic valve, the main cause of aortic stenosis at younger ages, can be found in several members of a family. If you have a bicuspid valve, especially with widening of the aorta, your doctor may suggest echocardiography for your parents, siblings, and children so any abnormality is detected earlier.
Sources and Medical Review
Translated from the Indonesian edition medically reviewed by dr. Suko Adiarto, Sp.JP(K), Ph.D..
Sources as cited in the Indonesian edition.
- Vahanian A, Beyersdorf F, Praz F, Milojevic M, Baldus S, Bauersachs J, et al. 2021 ESC/EACTS Guidelines for the management of valvular heart disease. Eur Heart J. 2022;43(7):561-632.
- Praz F, et al. 2025 ESC/EACTS Guidelines for the management of valvular heart disease. Eur Heart J. 2025;46(44):4635-4736.
- Otto CM, Nishimura RA, Bonow RO, Carabello BA, Erwin JP 3rd, Gentile F, et al. 2020 ACC/AHA Guideline for the Management of Patients With Valvular Heart Disease: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation. 2021;143(5):e72-e227.
- Baumgartner H, Hung J, Bermejo J, Chambers JB, Edvardsen T, Goldstein S, et al. Recommendations on the Echocardiographic Assessment of Aortic Valve Stenosis: A Focused Update from the European Association of Cardiovascular Imaging and the American Society of Echocardiography. J Am Soc Echocardiogr. 2017;30(4):372-392.
- Mack MJ, Leon MB, Thourani VH, Makkar R, Kodali SK, Russo M, et al. Transcatheter Aortic-Valve Replacement with a Balloon-Expandable Valve in Low-Risk Patients. N Engl J Med. 2019;380(18):1695-1705.
- Généreux P, et al. Transcatheter Aortic-Valve Replacement for Asymptomatic Severe Aortic Stenosis. N Engl J Med. 2025;392(3):217-227.
Doctors Who Treat This Condition

dr. BRM Ario S. Kuncoro, Sp.JP(K)
Echocardiography & Cardiovascular Imaging
Cardiovascular Diagnostic Center +2 centers
Clinical focusAdvanced and 3D Echocardiography · Transesophageal Echocardiography
View Profile
dr. Widya T. Suwatri, Sp.BTKV, Subsp. JD(K)
Adult Cardiac Surgery
Advanced Cardiovascular Surgical Care +1 center
Clinical focusMinimally Invasive Cardiac Surgery · Coronary Artery Bypass Surgery
View Profile
dr. Suko Adiarto, Sp.JP(K), Ph.D.
Interventional Cardiology
Vascular Diagnostic and Therapeutic Center +1 center
Clinical focusCoronary Intervention · Peripheral Vascular Intervention
View Profile