Quick answer
Dual antiplatelet therapy (DAPT) combines two antiplatelet medications, usually aspirin and a P2Y12 inhibitor, to reduce blood clot formation. It is prescribed for certain cardiovascular conditions, including after a heart attack or coronary stent placement. Doctors determine the medication combination and treatment duration based on clotting and bleeding risks. DAPT should never be discontinued without medical guidance.
See sourcesDAPT is a combination of two antiplatelet medications that may be prescribed after a heart attack or coronary stent placement. For patients who have recently undergone treatment, receiving a prescription containing two medications with similar functions may raise several questions. Why do both medications need to be taken together? How long should treatment continue? Are they still necessary when you start feeling better?
DAPT stands for Dual Antiplatelet Therapy. This treatment helps reduce blood clot formation by inhibiting platelet activity. Platelets are blood components involved in the clotting process. In certain conditions, DAPT plays an important role in reducing the risk of another heart attack or blood clot formation inside a coronary stent.
However, the benefits of DAPT must be balanced against potential side effects, particularly bleeding. For this reason, the medications prescribed and the duration of treatment are not necessarily the same for every patient.
This article will help you and your family understand the purpose of DAPT, the medications used, treatment duration, side effects, and important considerations during therapy. With accurate information, you can be better prepared to discuss appropriate heart care with your doctor.
What Is DAPT?
DAPT is a combination of two antiplatelet medications designed to inhibit platelet activity and help reduce blood clot formation. It is an important part of treatment for several cardiovascular conditions, particularly acute coronary syndrome and care following percutaneous coronary intervention (PCI), a procedure used to open narrowed or blocked coronary arteries.
Under normal circumstances, blood clotting helps the body stop bleeding when an injury occurs. However, a clot that forms inside a coronary artery can obstruct blood flow and the delivery of oxygen to the heart muscle. In certain conditions, antiplatelet medications help reduce the risk of these clots forming.
What Does Dual Antiplatelet Therapy Mean?
The word dual means two, while antiplatelet refers to medications that inhibit platelet activity. Dual antiplatelet therapy therefore involves two medications that work through different but complementary mechanisms.
Platelets play an important role when blood vessels are injured. They can adhere to the injured area, become activated, and gather together to form an initial clot. This process is necessary to stop bleeding, but it can become problematic when it occurs inappropriately within the coronary arteries.
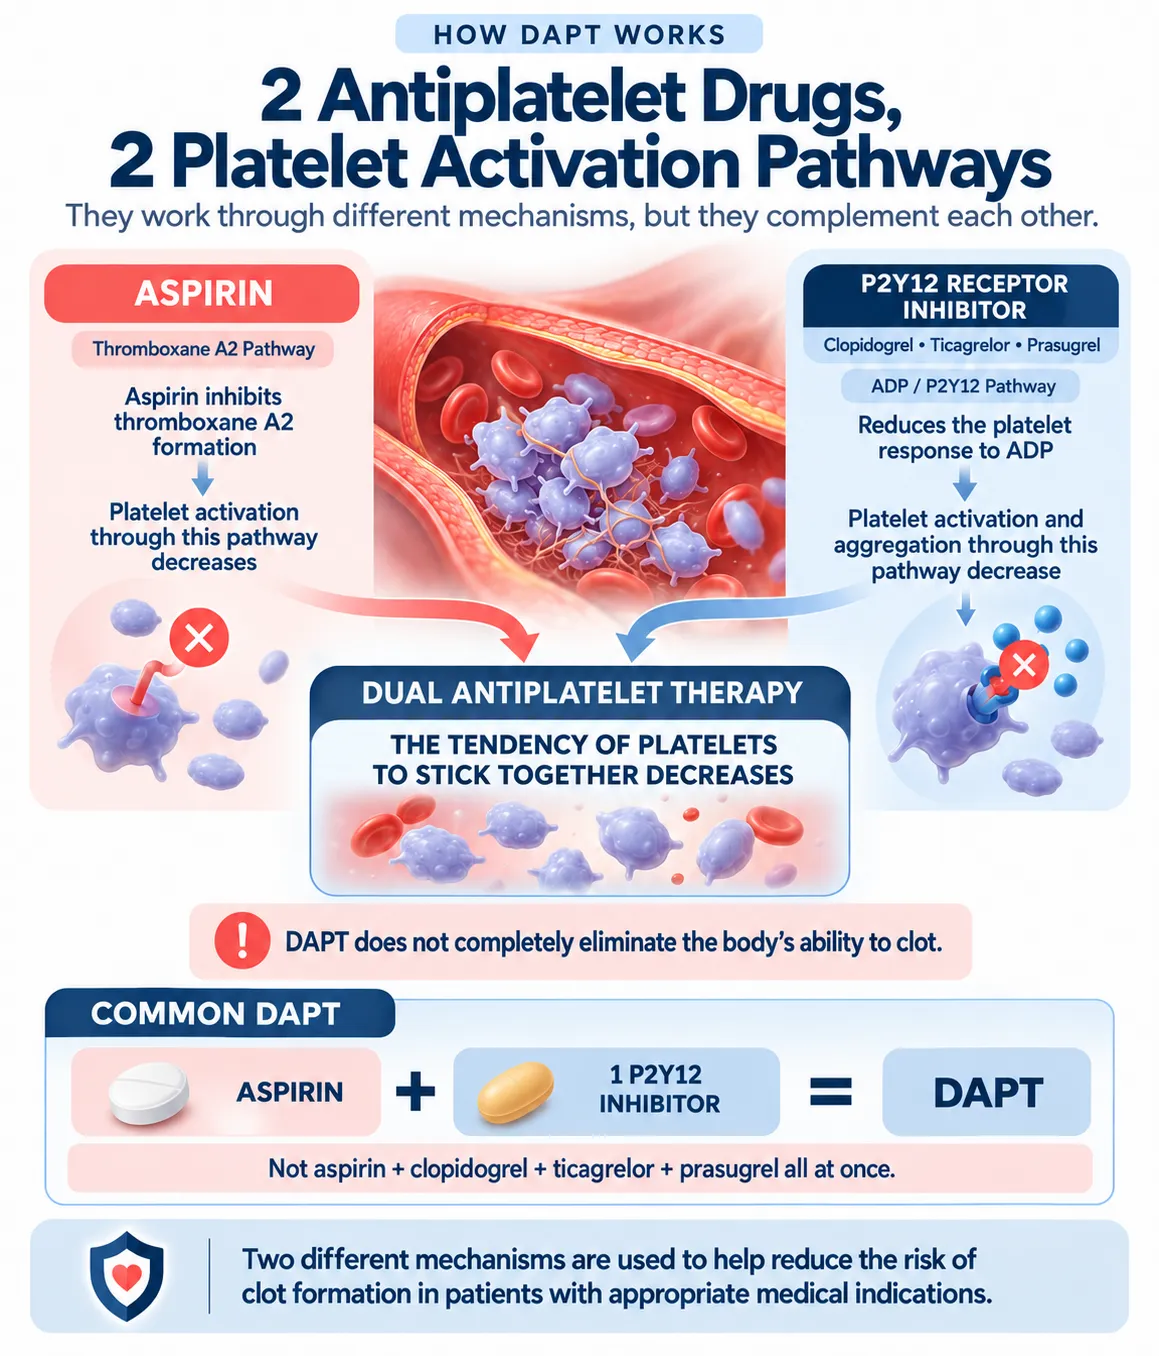
By inhibiting two pathways of platelet activation, DAPT helps reduce the tendency of platelets to stick together. This treatment does not completely eliminate the body’s ability to form blood clots. Therefore, its benefits in preventing unwanted clot formation must also be weighed against the risk of bleeding.
What Is the Difference Between Antiplatelets and Anticoagulants?
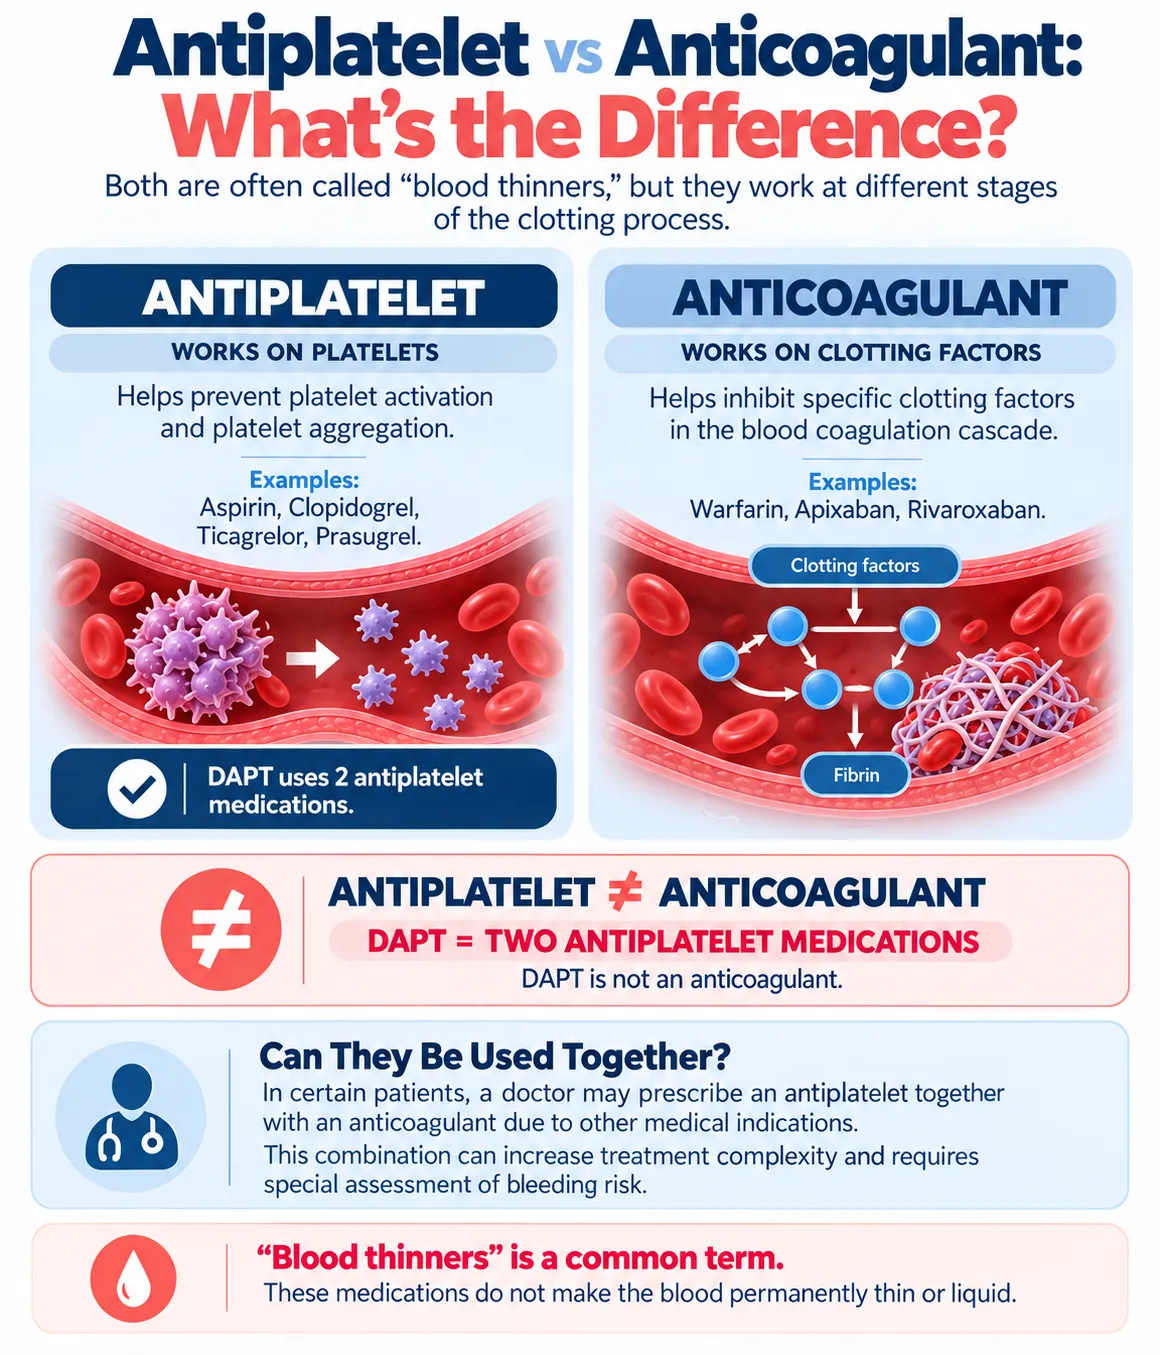
Antiplatelet and anticoagulant medications are often referred to as “blood thinners” in everyday conversation. While this term makes communication easier, neither type of medication literally makes the blood thinner.
The difference lies in which part of the blood clotting process each medication affects.
| Medication Class | General Mechanism of Action | Examples |
|---|---|---|
| Antiplatelets | Inhibit platelet activation and aggregation | Aspirin, clopidogrel, ticagrelor, prasugrel |
| Anticoagulants | Inhibit factors involved in the blood clotting cascade | Warfarin, apixaban, rivaroxaban |
DAPT combines two antiplatelet medications, not two anticoagulants. In certain patients, such as those who require anticoagulants for particular heart rhythm disorders, doctors may need to combine several antithrombotic medications. However, these combinations increase treatment complexity and require careful assessment of bleeding risk.
Understanding this distinction is important so that patients do not assume all medications used to prevent blood clots are interchangeable.
Uses and Benefits of DAPT
The primary purpose of DAPT is to help reduce the risk of events caused by blood clot formation in patients with specific medical indications. In the treatment of coronary artery disease, its benefits are particularly related to protection against thrombotic events following acute coronary syndrome or coronary stent placement.
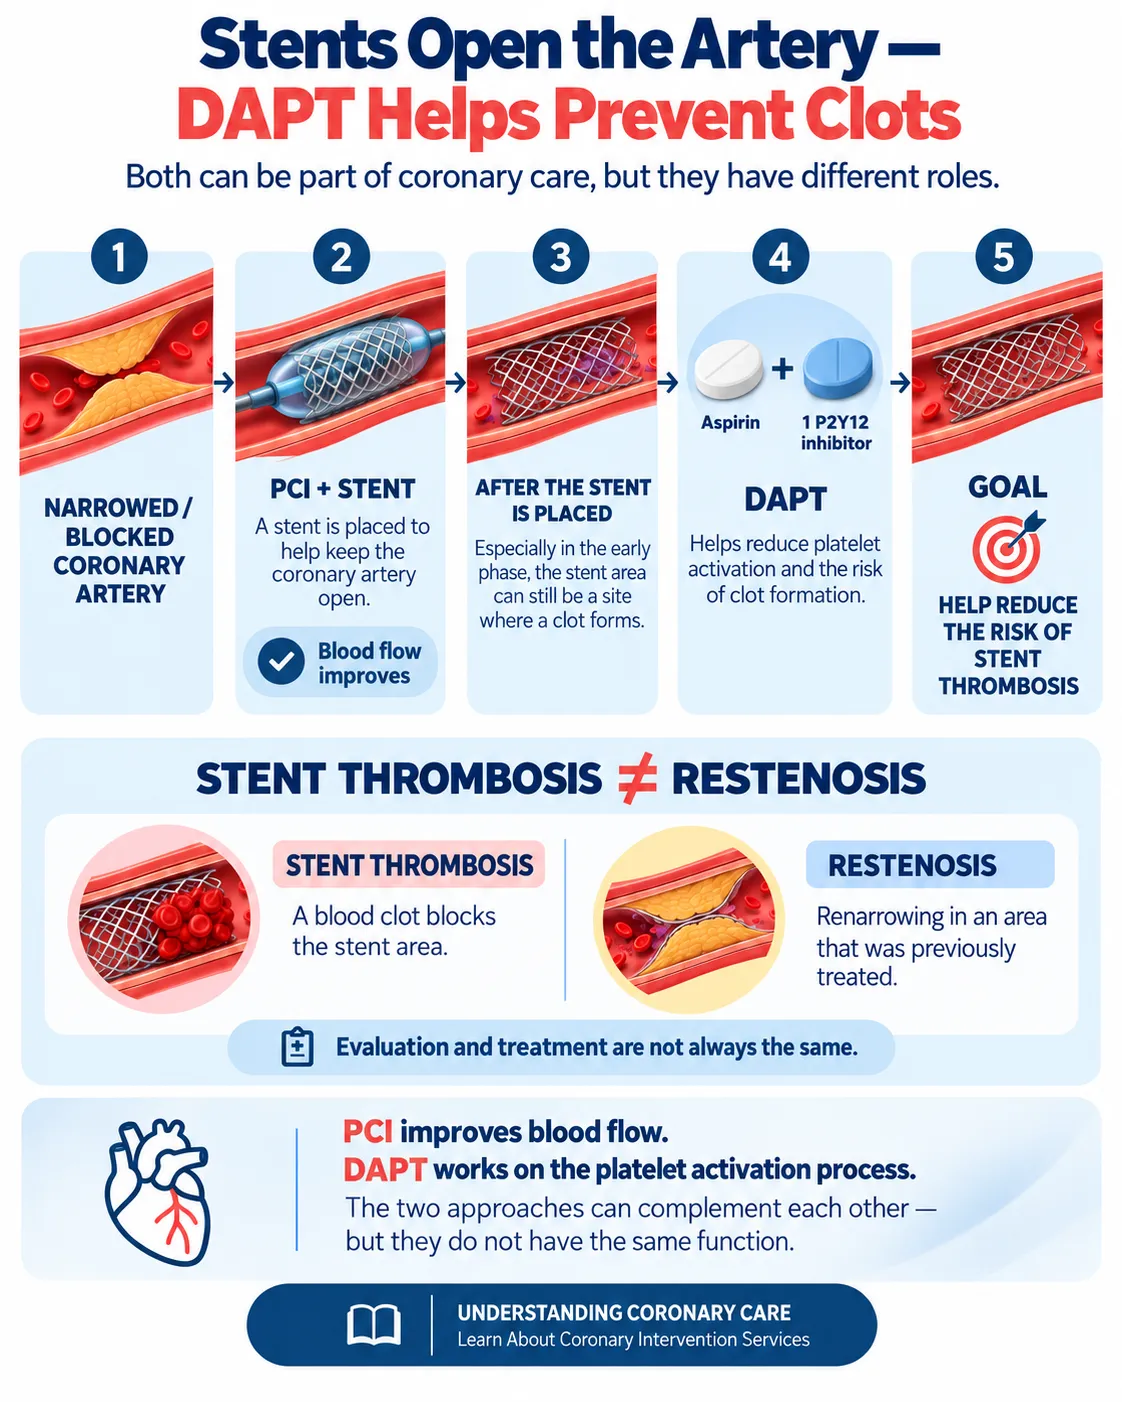
To understand these benefits, it is important to distinguish between opening a narrowed blood vessel and preventing blood clots from forming. PCI aims to improve blood flow through a coronary artery that has become narrowed or blocked. DAPT, meanwhile, acts on the platelet activation process that can lead to clot formation.
These two approaches can complement each other, but they do not serve the same purpose.
How Does DAPT Work?
When the inner lining of a blood vessel is injured or an atherosclerotic plaque ruptures, platelets can become activated. These activated platelets then stick together and contribute to blood clot formation.
In DAPT, aspirin inhibits the production of thromboxane A2, a substance involved in platelet activation. The second medication, a P2Y12 receptor inhibitor, reduces the response of platelets to adenosine diphosphate (ADP), one of the signals that triggers platelet activation.
By inhibiting two platelet activation pathways, DAPT helps reduce the risk of blood clot formation in patients with appropriate medical indications.
However, DAPT does not directly remove atherosclerotic plaque, dissolve existing blood clots, or open blocked coronary arteries. Its primary role is to help reduce the risk of clot formation. Managing cholesterol, blood pressure, diabetes, smoking, and other risk factors remains an important part of heart care.
Why Is DAPT Important After Coronary Stent Placement?
A coronary stent is a small mesh-like device placed inside a coronary artery. Once implanted, the stent helps keep the artery open, allowing blood to flow more effectively to the heart muscle.
However, particularly during the early period after the procedure, blood clots can still form around the stent. When a clot blocks this area, the condition is known as stent thrombosis. If it occurs, blood flow to the heart muscle can be disrupted suddenly.
DAPT helps reduce the likelihood of this clot formation. This is one reason doctors emphasize the importance of taking antiplatelet medications according to the prescribed schedule after stent placement.
Stent thrombosis should be distinguished from restenosis, which refers to the re-narrowing of a blood vessel in an area that has previously been treated. These are different conditions, so their evaluation and management may also differ.
What Are the Benefits of DAPT After a Heart Attack?
A heart attack often occurs when blood flow through a coronary artery is suddenly obstructed, for example, by a clot forming on a ruptured atherosclerotic plaque.
After the acute condition has been treated, reducing the risk of further clot formation remains important. For patients with acute coronary syndrome, DAPT is one of the key treatment strategies used to reduce the risk of cardiovascular events caused by thrombotic processes.
However, DAPT is not the only component of care following a heart attack. Doctors may also prescribe treatments to manage cholesterol, blood pressure, and other risk factors. Cardiac rehabilitation and lifestyle changes also contribute to recovery and the prevention of recurrent events.
Who Needs DAPT?
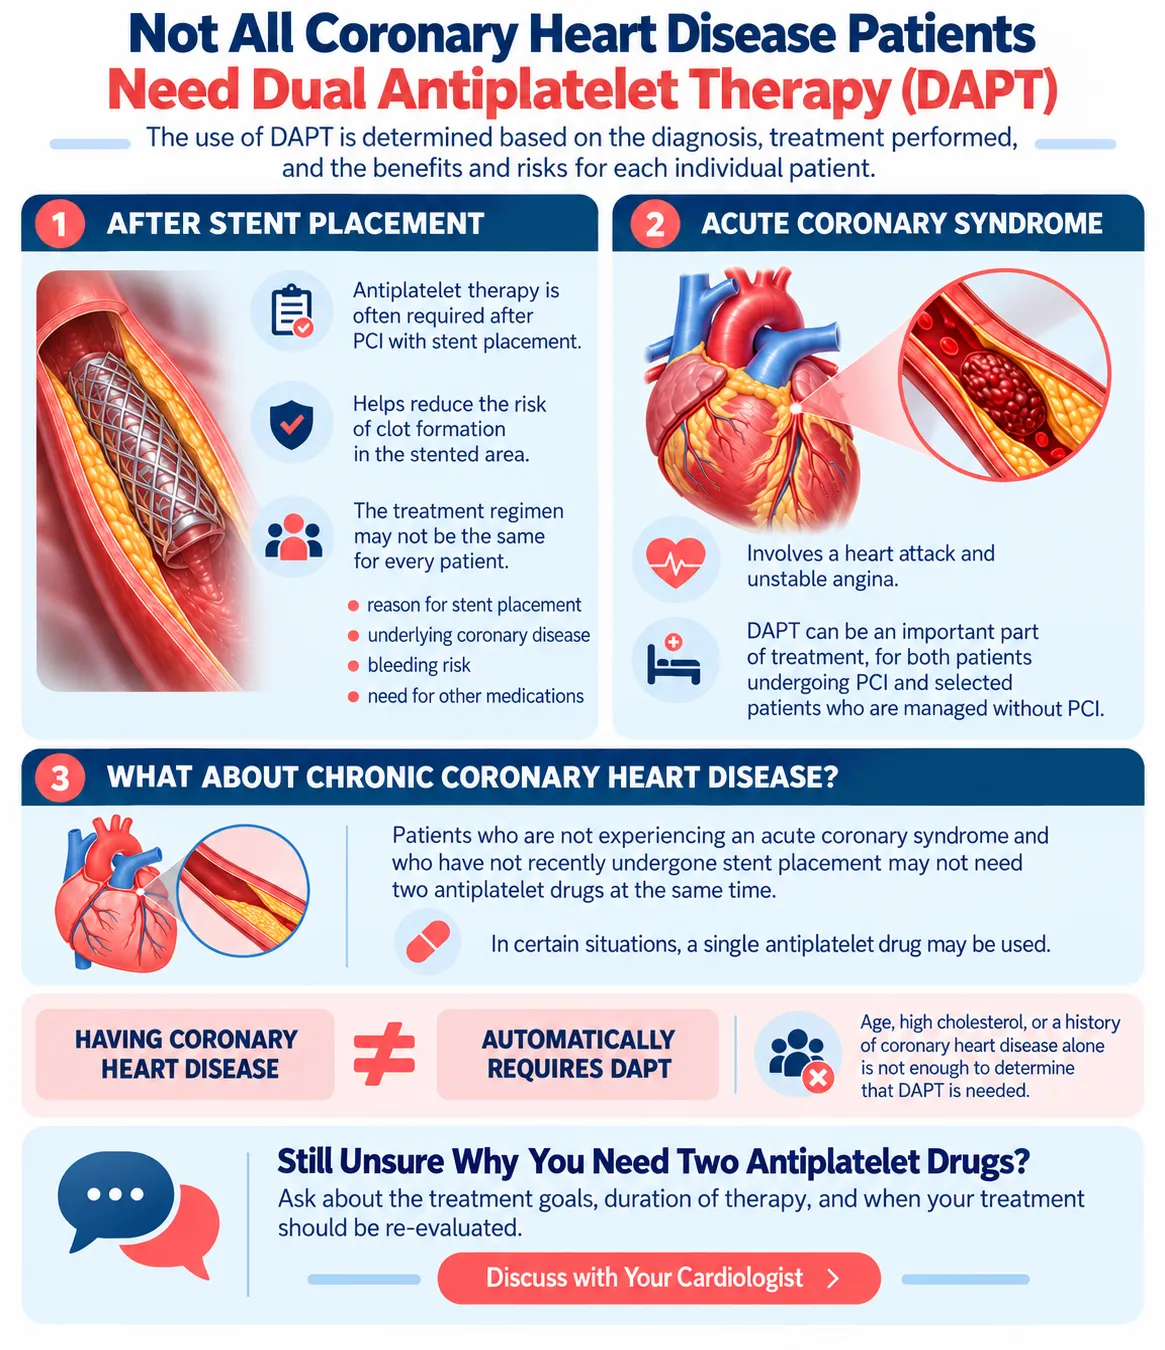
Not every patient with coronary artery disease needs DAPT. Doctors recommend this treatment based on the diagnosis, procedures performed, and the expected benefits and risks for each patient.
The two situations most commonly associated with DAPT in coronary care are following stent placement and in patients with acute coronary syndrome.
Patients After Coronary Stent Placement
Patients who undergo PCI with stent placement usually require antiplatelet therapy after the procedure. The goal is to help prevent blood clots that could interfere with blood flow around the stent.
However, the prescribed regimen is not necessarily identical for everyone. Doctors consider why the stent was implanted, the underlying coronary disease, bleeding risk, and the need for other medications.
Before leaving the hospital, patients should therefore understand the names of their medications, how to take them, and when their treatment will be reassessed.
Patients With Acute Coronary Syndrome
Acute coronary syndrome refers to a group of conditions in which blood flow to the heart muscle is suddenly reduced. These conditions include heart attacks and unstable angina.
DAPT can be an important part of treatment for acute coronary syndrome, both in patients undergoing PCI and in certain patients receiving medical treatment without PCI.
The choice of antiplatelet medications and treatment strategy depends on the patient’s condition and the management plan established by the doctor.
Do All Patients With Coronary Artery Disease Need DAPT?
No.
Patients with chronic coronary artery disease who are not currently experiencing acute coronary syndrome and have not recently undergone stent placement do not necessarily need two antiplatelet medications at the same time.
In certain circumstances, doctors may prescribe a single antiplatelet medication as part of cardiovascular event prevention. Other situations may require a combination of medications for a specified period.
This decision cannot be made based solely on age, high cholesterol, or a history of heart disease. Medical examination and clinical evaluation are still necessary.
Medications Used in DAPT
DAPT generally involves aspirin combined with one P2Y12 receptor inhibitor. These medications act on different platelet activation pathways.
Commonly used medications include aspirin, clopidogrel, ticagrelor, and prasugrel. Knowing their generic names can help patients understand their prescriptions, but this does not mean the medications can be selected or substituted without medical guidance.
Aspirin as a Component of DAPT
Aspirin is known as a medication used for various medical purposes. In cardiovascular treatment, low-dose aspirin is used as an antiplatelet medication to help inhibit platelet activation.
Aspirin works by inhibiting the production of thromboxane A2, one of the substances involved in platelet activation. When used as part of DAPT, aspirin is combined with another medication that works through a different pathway.
Taking aspirin as prescribed by a doctor for heart disease differs from independently starting daily aspirin for prevention. Do not begin taking aspirin every day without consulting a doctor, as its benefits and bleeding risks must be assessed according to your individual circumstances.
Clopidogrel, Ticagrelor, and Prasugrel
Clopidogrel, ticagrelor, and prasugrel belong to a class of medications called P2Y12 receptor inhibitors. These medications inhibit platelet responses to ADP, one of the signals that triggers platelet activation and aggregation.
Although they belong to the same medication class, they have different characteristics and safety considerations. The choice may be influenced by the patient’s clinical condition, coronary intervention strategy, history of bleeding, previous stroke or transient ischemic attack (TIA), and other factors. Prasugrel must not be given to patients with a history of stroke or TIA.
For example, the 2025 AHA/ACC guideline for acute coronary syndromes gives preference to ticagrelor or prasugrel over clopidogrel in patients undergoing PCI when clinically appropriate and when there are no contraindications. However, these medications are not necessarily suitable for every patient.
How Do Doctors Choose the Medication Combination?
Doctors consider more than how strongly a medication inhibits platelet activity. They also need to assess whether a patient has conditions that increase bleeding risk or requires other treatments that may influence the choice of antiplatelet medications.
A history of heart attack, PCI findings, previous stroke or TIA, kidney problems, prior bleeding, and other medications being taken may all be part of the assessment.
| Medication Class | Examples | Role in DAPT |
|---|---|---|
| Aspirin | Aspirin | Inhibits platelet activation through the thromboxane A2 production pathway |
| P2Y12 receptor inhibitors | Clopidogrel, ticagrelor, prasugrel | Inhibit platelet responses to ADP |
Note: In standard DAPT, aspirin is combined with one P2Y12 receptor inhibitor, not all P2Y12 inhibitors simultaneously.
How Long Should DAPT Be Taken?
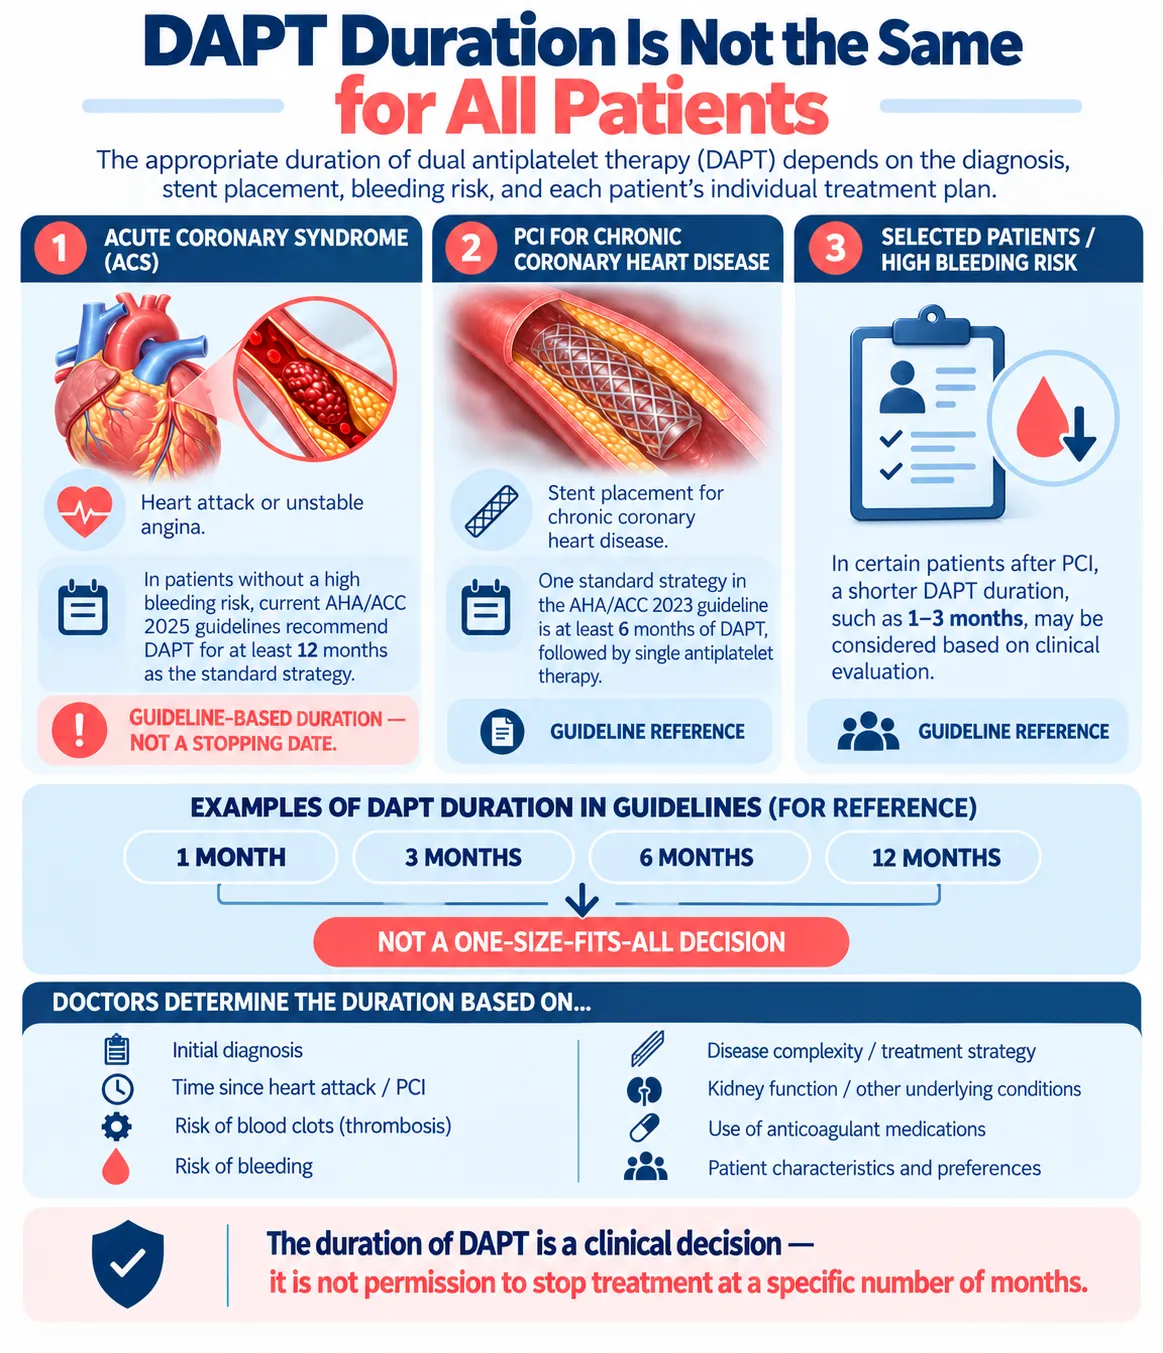
The duration of DAPT is not the same for every patient. Some patients receive treatment for several months, while others may need a longer duration or a different medication strategy.
The determining factors are not simply whether the patient feels healthy again, but the original diagnosis, previous procedures, risk of blood clot formation, and risk of bleeding.
Clinical guidelines provide reference points for treatment duration. However, these recommendations should be understood as a basis for medical decision-making, not permission to stop medications once a particular period has passed.
DAPT Duration for Acute Coronary Syndrome, Including Heart Attacks
For patients with acute coronary syndrome who are not at high risk of bleeding, the 2025 AHA/ACC guideline recommends DAPT for at least 12 months as the standard strategy.
This period is intended to provide antithrombotic protection during the phase following an acute event, when the risk of further cardiovascular events remains a concern.
However, not every patient can follow the same strategy. For those at high risk of bleeding, doctors may consider different approaches, including shortening the period of treatment with two medications or switching to a particular regimen in accordance with clinical guidelines.
Patients should therefore ask about the treatment duration specifically planned for their own condition.
DAPT Duration After Coronary Stent Placement
The duration of DAPT after stent placement depends on why the procedure was performed.
For patients with chronic coronary disease undergoing PCI, the 2023 AHA/ACC guideline describes aspirin and clopidogrel for six months, followed by single antiplatelet therapy, as a standard strategy.
The 2024 ESC guideline also discusses shorter DAPT options of one to three months for selected patients after PCI, particularly those with a high bleeding risk or without a high ischemic risk. These decisions must be based on a doctor’s evaluation.
When a stent is implanted in the context of acute coronary syndrome, treatment duration follows the recommendations and considerations for that acute condition, which generally differ from those for elective PCI in chronic coronary disease.
For certain patients, doctors may shorten DAPT and then continue treatment with a single antiplatelet medication to reduce bleeding risk. Conversely, other patients may need a longer antithrombotic protection strategy based on an assessment of the expected benefits and risks.
Therefore, two patients who have both undergone coronary stent placement will not necessarily receive the same treatment schedule.
| Clinical Situation | Guideline-Based Duration | Important Considerations |
|---|---|---|
| Acute coronary syndrome without high bleeding risk | Generally at least 12 months | Duration may be adjusted by the doctor |
| PCI for chronic coronary disease | Generally 6 months, followed by single antiplatelet therapy | May be shorter in selected patients |
| High bleeding risk or a need for anticoagulation | Requires a tailored strategy | Duration is determined through medical evaluation |
This table is intended for educational purposes and should not be used as instructions to change or stop medication independently.
Why Does DAPT Duration Differ Between Patients?
When determining how long DAPT should continue, doctors balance two important considerations.
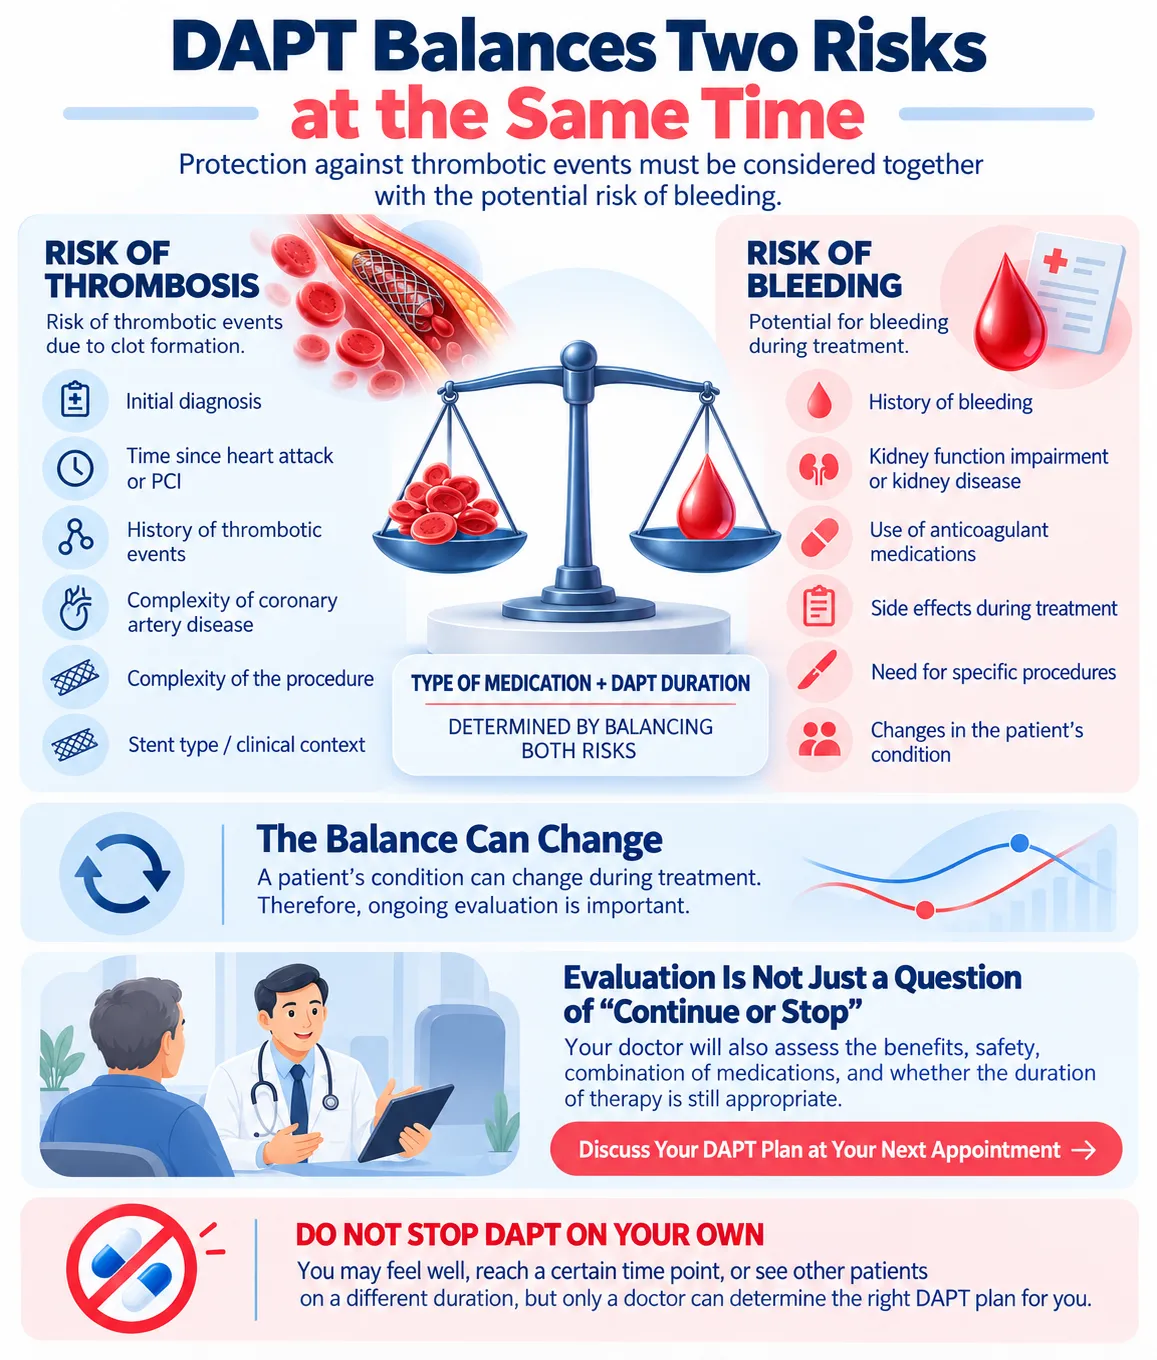
On one hand, DAPT helps reduce the risk of events caused by blood clot formation. On the other, using two antiplatelet medications can increase bleeding risk. Doctors must therefore weigh these risks when choosing the medication combination and treatment duration.
Factors they may consider include:
- The original diagnosis and the time elapsed since a heart attack or PCI.
- A history of thrombotic events or bleeding.
- The complexity of coronary disease and the procedure performed.
- Kidney conditions or other coexisting diseases.
- The use of anticoagulant medications for other indications.
- Changes in the patient’s condition during treatment.
This balance may change over time. That is why regular treatment evaluation is an important part of follow-up care.
Does DAPT Have to Be Taken for Life?
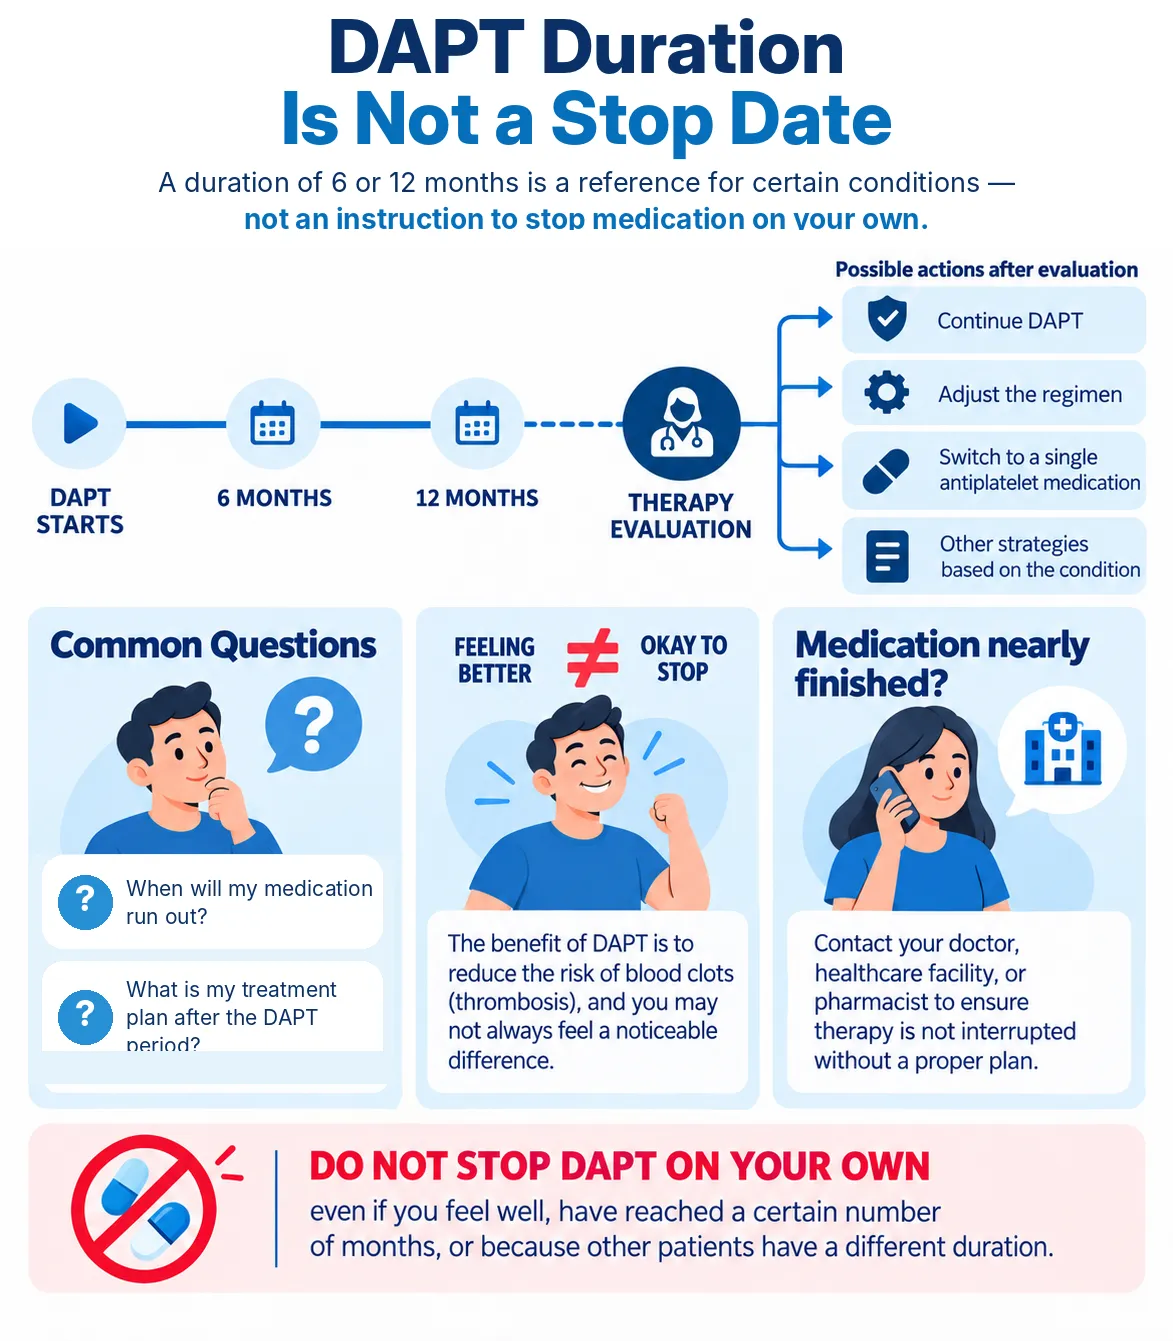
DAPT does not automatically need to be continued for life. After a certain treatment period, doctors may reassess whether a patient still needs two antiplatelet medications or can transition to another regimen.
However, completing the DAPT period does not necessarily mean that all antiplatelet medications should be stopped. For many patients with coronary artery disease, single antiplatelet therapy remains part of long-term care.
Therefore, the question to ask during a follow-up appointment is not simply, “When will I finish my medication?” but rather, “What is my treatment plan after the DAPT period ends?”
Risks of Stopping DAPT Without Medical Guidance
Feeling healthier after coronary stent placement or a heart attack is certainly a positive development. However, an improvement in symptoms does not automatically mean that antiplatelet treatment can be stopped.
DAPT works by reducing the likelihood of blood clots forming. Unlike relief from chest pain, this benefit may not be directly noticeable. As a result, patients may feel healthy even while they still need the protection provided by their prescribed treatment.
What Happens If DAPT Is Stopped Too Early?
In patients with certain conditions, stopping DAPT before the planned time may increase the risk of blood clot formation. Following stent placement, one complication of particular concern is stent thrombosis, especially during periods when the risk of clot formation remains high.
This risk cannot be assessed simply by counting the days since the procedure. The type of heart condition, treatment course, and patient’s clinical circumstances all influence the decision.
Do not stop DAPT because you feel recovered or because another patient has been prescribed a different treatment duration. If your medication supply is running low, promptly contact your doctor, healthcare facility, or pharmacy to avoid an interruption in treatment.
What If a Patient Wants to Stop DAPT Because of Side Effects?
Symptoms experienced during treatment deserve attention. Easy bruising, recurrent nosebleeds, or digestive problems may cause discomfort and lead patients to question whether they should continue their medications.
The appropriate step is to discuss these concerns with your doctor rather than stopping treatment or reducing the dose on your own. Your doctor can investigate possible causes, assess their severity, and determine whether treatment adjustments are needed.
If signs of serious bleeding occur, do not wait for your routine appointment. Seek emergency medical attention immediately.
Side Effects and Risks of DAPT
Like other treatments, DAPT has both benefits and risks that patients need to understand. The most significant risk is bleeding because antiplatelet medications inhibit one part of the blood clotting process.
Not every patient will experience side effects. Some may develop mild symptoms, while certain conditions require immediate assessment. Understanding the difference helps patients respond appropriately without having to guess what is causing their symptoms.
Bruising, Nosebleeds, and Bleeding
Patients taking antiplatelet medications may bruise more easily, experience nosebleeds, or notice that bleeding from small cuts takes longer to stop.
These symptoms do not always indicate a medical emergency. However, new symptoms, symptoms that recur, become more severe, or interfere with daily activities should be reported to your doctor.
Also pay attention to whether the symptoms occur alongside other changes, such as unusual weakness, dizziness, or signs of blood loss. Information about when the symptoms began and how frequently they occur can help your doctor evaluate them.
Can DAPT Cause Stomach Problems?
Antiplatelet medications, particularly aspirin, may be associated with gastrointestinal problems. The concern is not limited to stomach discomfort but also includes the possibility of gastrointestinal bleeding.
Patients with a history of stomach ulcers, previous gastrointestinal bleeding, or use of other medications that increase bleeding risk should inform their doctor.
For patients at risk of gastrointestinal bleeding, doctors may prescribe medications from a class called proton pump inhibitors (PPIs) to help protect the gastrointestinal tract.
Omeprazole and esomeprazole can reduce the activation of clopidogrel through drug interactions. If a PPI is necessary, doctors may consider a more appropriate alternative, such as pantoprazole.
Do not start, switch, or stop taking stomach medications without consulting your doctor or pharmacist.
Other Side Effects to Watch For
In addition to bleeding and digestive problems, some patients taking ticagrelor may experience shortness of breath. This symptom should be evaluated by a doctor to determine whether it is related to the medication or an underlying heart or lung condition.
If shortness of breath develops suddenly, is severe, or occurs with chest pain, seek immediate medical attention.
Signs of Serious Bleeding
Certain symptoms should not be dismissed as ordinary side effects, especially if they suggest severe bleeding or a sudden blood vessel-related problem.
Gastrointestinal bleeding, bleeding that is difficult to stop, or sudden neurological symptoms are examples of conditions that should never be ignored. The following warning signs require prompt attention.
These symptoms can have various causes and are not always the result of DAPT. However, in someone taking antiplatelet medications, they require urgent medical assessment.
Important: If you notice blood in your urine, contact your doctor or healthcare facility promptly for medical evaluation, even if the amount appears small. If bleeding is heavy or your condition is worsening, go to the emergency department immediately. Do not stop DAPT on your own.
What Should You Do If You Experience Side Effects?
The appropriate response depends on the type and severity of the symptoms.
For non-emergency symptoms, such as newly developed bruising or recurrent nosebleeds that have stopped, contact your treating doctor. Record your symptoms, the medications you are taking, and any changes you have noticed since starting treatment.
If you experience symptoms suggestive of serious bleeding, seek immediate medical attention. Do not attempt to manage the situation simply by changing your medication schedule yourself.
Most importantly, treatment safety must be assessed alongside its benefits. Changes to the medication regimen should be made through medical evaluation, not based on a single symptom or general information found online.

Staying Safe During DAPT
Successfully following long-term treatment involves more than understanding what your medications do. Simple habits, such as keeping track of medication schedules, recording changes in symptoms, and preparing for follow-up appointments, can also help patients follow their treatment plans more consistently.
The Importance of Taking Medications on Schedule
If you take several medications with different dosing schedules, use a reminder system that works for you, such as a phone alarm, daily notes, or a pill organizer arranged according to your prescription.
Do not assume your medication schedule should be the same as that of a family member or another patient. Even when diagnoses are similar, medication combinations and dosing instructions may differ.
If your medication supply is running low before your next appointment, promptly contact your healthcare facility or pharmacy according to your doctor’s instructions to prevent an unplanned interruption.
What If You Miss a DAPT Dose?
The appropriate response to a missed dose depends on the medication, when the dose was missed, and the treatment instructions you have received.
Because missed-dose instructions can differ between medications, do not apply the same rule to every DAPT regimen. Do not take a double dose to make up for a missed one. If you are unsure what to do, contact your doctor or pharmacist and provide the medication name and the time the dose was missed.
If you frequently forget to take your medications, discuss this during your follow-up appointment. Your doctor or pharmacist can help explain reminder strategies and the appropriate steps to take when a dose is missed.
Medications and Supplements That Require Attention
While receiving DAPT, inform your doctor and pharmacist about all medications you take, including over-the-counter medicines, supplements, and herbal products.
Certain nonsteroidal anti-inflammatory drugs, such as ibuprofen, can increase bleeding risk when used with antiplatelet medications. Anticoagulants, certain stomach medications, and herbal products may also require special consideration.
Do not add pain relievers or other medications to your regimen before confirming their safety with your doctor or pharmacist.
This does not mean that patients must stop taking all their other medications. Rather, providing a complete medication list helps healthcare professionals assess treatment combinations more safely.
Should DAPT Be Stopped Before Surgery or Tooth Extraction?
Do not stop DAPT on your own before a medical or dental procedure.
Before surgery, tooth extraction, or any procedure that may cause bleeding, inform your doctor and dentist that you are taking antiplatelet medications.
For many dental procedures, antiplatelet medications do not need to be changed. However, each patient’s needs must still be assessed based on the procedure, medical history, and the risks of bleeding and clot formation.
If medication changes are considered necessary, the decision should be coordinated between the healthcare professionals performing the procedure and the doctor who prescribed the antiplatelet therapy.
How Families Can Support Patients
Treatment after a heart attack or stent placement may involve several medications, follow-up appointments, and changes to daily habits. In these situations, family support can be helpful.
Caregivers or family members can provide agreed-upon medication reminders, help prepare questions for appointments, or accompany patients when needed.
However, meaningful support should continue to respect the patient’s independence. The goal is not to take over every decision, but to ensure that patients feel supported and have access to the information they need.
One simple step is to keep an updated medication list containing dosing instructions, relevant procedure history, and contact information for healthcare services. This list can be useful during follow-up appointments or when urgent medical attention is needed.

When Should DAPT Be Reassessed?
DAPT needs to be reassessed to ensure that the treatment plan remains appropriate for the patient’s condition. Follow-up appointments are not only about determining whether medication is still necessary, but also about evaluating whether the benefits, safety, and overall treatment needs remain appropriately balanced.
Reviewing Treatment Duration and Medication Combinations
During follow-up visits, your doctor may review changes in your heart condition, symptoms you have experienced, and medications you are currently taking.
Based on this evaluation, your doctor can determine whether DAPT should continue as planned, be adjusted, or transition to another regimen at the appropriate time.
Therefore, if you are approaching the end of the treatment period previously discussed with your doctor, make sure the next steps are clear before making any medication changes.
Information to Bring to Your Follow-Up Appointment
To make your consultation more productive, prepare the following information:
- The names of all medications you take and their dosing instructions.
- Your history of heart attack or the date of stent placement, if applicable.
- Your hospital discharge summary, procedure report, or available test results.
- Notes about symptoms such as nosebleeds, bruising, or stomach discomfort.
- A list of over-the-counter medications and supplements you use.
- Questions about DAPT duration and your subsequent treatment plan.
This preparation can help focus the discussion with your doctor on your individual needs.
When Should You Consider a Second Opinion?
A second medical opinion may be considered when a patient receives different treatment recommendations or needs further clarification about the diagnosis, benefits, and risks of therapy.
For example, a patient may receive different recommendations about DAPT duration from two doctors. This does not necessarily mean that one recommendation is incorrect. Clinical circumstances, procedure history, bleeding risk, and test results can influence each doctor’s assessment.
A second opinion can provide additional information about the most appropriate treatment options. Bring your medical records, procedure summary, and a complete medication list. During this process, do not stop treatment without guidance from your treating doctor.
You can learn more in Heartology’s article about when to consider a second opinion after coronary stent placement.

Conclusion
DAPT is a combination of two antiplatelet medications that helps reduce the risk of blood clot formation in certain cardiovascular conditions, including after a heart attack or coronary stent placement.
However, the benefits of treatment must be balanced against bleeding risks. Therefore, the medication combination and duration of DAPT are determined according to each patient’s condition.
By understanding the purpose of therapy, following medication instructions, recognizing potential side effects, and attending recommended follow-up appointments, you can take a more active role in your heart care. If you still have questions, discuss them with your doctor so that every decision is based on your individual medical condition.
Heart Care Consultations at Heartology
After a heart attack or coronary stent placement, heart care does not end when patients leave the hospital. Monitoring, medication reviews, and appropriate follow-up are important parts of the treatment plan.
At Heartology Cardiovascular Hospital, the cardiovascular specialist team provides services, including the Interventional Cardiology Center, to help patients receive care tailored to their medical needs.
If you have questions about your medications, DAPT duration, or symptoms experienced during treatment, discuss them with a cardiologist. A consultation can help ensure that your treatment plan and follow-up evaluation remain appropriate for your condition.
Medical Information: This article is intended for educational purposes and does not replace examination, diagnosis, or treatment instructions from a doctor. Decisions to start, change, or stop medications must be based on an evaluation by a healthcare professional.
Keep as a reminder
Checklist before Your Consultation
Tick what you have prepared.
0 of 6 items checked
Checks are kept only while this page is open.
Next step
Want to Find the Right Doctor?
Learn about doctors by specialty and clinical focus before you decide on your next step.
The information on this page is for educational purposes and does not replace medical consultation, diagnosis, or treatment. For any health concerns, please consult a doctor directly.
Doctors Related to This Topic

Dr. dr. Dafsah A. Juzar, Sp.JP(K)
Interventional Cardiology
Coronary Intervention Procedures +1 center
Clinical focusComplex Coronary Intervention · Cardiac Catheterization
View Profile
Dr. dr. Faris Basalamah, Sp.JP(K)
Interventional Cardiology
Coronary Intervention Procedures +1 center
Clinical focusComplex Coronary Intervention · Cardiac Electrophysiology
View Profile
Dr. dr. Jajang Sinardja, Sp.JP(K)
Interventional Cardiology
Coronary Intervention Procedures
Clinical focusAcute Coronary Syndrome · Primary Coronary Intervention
View ProfileFrequently Asked Questions.
Dual antiplatelet therapy often raises questions, particularly about the combination of medications used, treatment duration, potential side effects, and safety precautions. Below are answers to frequently asked questions from patients and their families to help clarify how DAPT works, what to expect during treatment, and which concerns should be discussed with a doctor.
Is DAPT the Same as Taking Blood Thinners?
DAPT belongs to a group of treatments commonly referred to as blood thinners. However, medically, DAPT is a combination of two antiplatelet medications. The term "blood thinners" is also used for anticoagulants, which work through a different mechanism.
Why Are Aspirin and Clopidogrel Taken Together?
Aspirin and clopidogrel inhibit platelet activity through different pathways. In certain conditions, combining these medications helps provide the antithrombotic protection a patient needs. They must be used according to a doctor's prescription.
Does DAPT Have to Be Taken for Life?
Not always. DAPT is often prescribed for a specific period and then reassessed. Some patients continue to need antiplatelet treatment afterward, but not necessarily with two medications simultaneously.
Can You Stop DAPT After Six Months?
This decision should not be made independently. Six months is one standard treatment duration in the context of PCI for chronic coronary disease, but it does not apply to every patient. Your doctor needs to confirm whether changing treatment is appropriate for your condition.
Is DAPT Still Necessary If You Feel Healthy?
It may still be necessary. DAPT is intended to help prevent thrombotic events, so its benefits are not always noticeable through changes in symptoms. Continue following your prescribed treatment plan until your doctor reassesses it.
Can DAPT Cause Gastrointestinal Bleeding?
DAPT can increase bleeding risk, including bleeding in the gastrointestinal tract. Inform your doctor if you have a history of stomach ulcers or bleeding. Vomiting blood or passing black stools requires prompt medical assessment.
What Should You Do If You Forget to Take Aspirin or Clopidogrel?
Follow the specific instructions for your prescribed medication or contact your doctor or pharmacist. Missed-dose instructions may differ between medications. Do not take a double dose based on your own assumptions.
Can You Have a Tooth Extracted While Taking DAPT?
Many dental procedures can be performed without stopping antiplatelet medications, but the decision must take into account the patient's condition and the planned procedure. Always inform your dentist and the doctor who prescribed DAPT before undergoing treatment.
Can Patients With Diabetes or Hypertension Take DAPT?
Diabetes and hypertension do not automatically prevent or require DAPT use. Doctors consider these conditions alongside the cardiac diagnosis, bleeding risk, and other medications before determining the treatment plan.
Can Patients Who Have Not Undergone Coronary Stent Placement Need DAPT?
Yes. DAPT may be prescribed for certain conditions, including some patients with acute coronary syndrome who do not undergo stent placement. The decision still depends on the diagnosis and the doctor's treatment plan.
Why Might Doctors Recommend Different DAPT Durations?
Different recommendations may arise from variations in clinical condition, procedure history, bleeding risk, or new information about the patient's health. Ask for an explanation of the reasoning behind the recommendation and make sure the treatment plan is clearly coordinated.
Sources and Transparency.

Reviewer
Translated from the Indonesian edition medically reviewed by Dr. med. dr. Denio A. Ridjab, Sp.JP(K), Cardiology and Vascular Medicine on October 22, 2026.
Sources as cited in the Indonesian edition.
- American Heart Association. (2025). Top Things to Know: 2025 Guideline for Acute Coronary Syndromes. Professional Heart Daily, American Heart Association.
- Virani SS, et al. (2023). 2023 AHA/ACC/ACCP/ASPC/NLA/PCNA Guideline for the Management of Patients With Chronic Coronary Disease: A Report of the American Heart Association/American College of Cardiology Joint Committee on Clinical Practice Guidelines. Journal of the American College of Cardiology, 82(9), 833–955.
- Vrints C, et al. (2024). 2024 ESC Guidelines for the Management of Chronic Coronary Syndromes. European Heart Journal, 45(36), 3415–3537.
- Gorog DA, et al. (2026). Antithrombotic Therapy for Secondary Prevention in Patients With Acute Coronary Syndromes Treated With Percutaneous Coronary Intervention: Options for Personalization to Reduce Bleeding or Ischaemic Risks. European Heart Journal – Acute Cardiovascular Care, 15(4), 337–363.
- American Heart Association. (2025). Types of Heart Medications. American Heart Association.
- National Health Service. (2025). Side Effects of Clopidogrel. NHS Medicines A to Z.
- National Health Service. (2025). How and When to Take Clopidogrel. NHS Medicines A to Z.
- NHS Specialist Pharmacy Service. (2023). Using Clopidogrel With Proton Pump Inhibitors (PPIs). Specialist Pharmacy Service, National Health Service.
- American Dental Association. (2022). Oral Anticoagulant and Antiplatelet Medications and Dental Procedures. ADA Oral Health Topics.
- Kementerian Kesehatan Republik Indonesia. (2024). Akses Darurat Medis 119 Kini Bisa Melalui SATUSEHAT Mobile. Kementerian Kesehatan RI.
- Rao SV, et al. (2025). 2025 ACC/AHA/ACEP/NAEMSP/SCAI Guideline for the Management of Patients With Acute Coronary Syndromes: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Journal of the American College of Cardiology, 85(22), 2135–2237.
- National Health Service. (2025). Taking Clopidogrel With Other Medicines and Herbal Supplements. NHS Medicines A to Z.
- South Tees Hospitals NHS Foundation Trust. (2025). Commonly Used Heart Medicines. Patient Information Leaflet, Version 3. South Tees Hospitals NHS Foundation Trust.
The information on this page is for educational purposes and does not replace medical consultation, diagnosis, or treatment. For any health concerns, please consult a doctor directly.
If you find information that needs clarifying, let us know through our Contact Us page.