
Quick answer
What Is Peripheral Artery Disease?
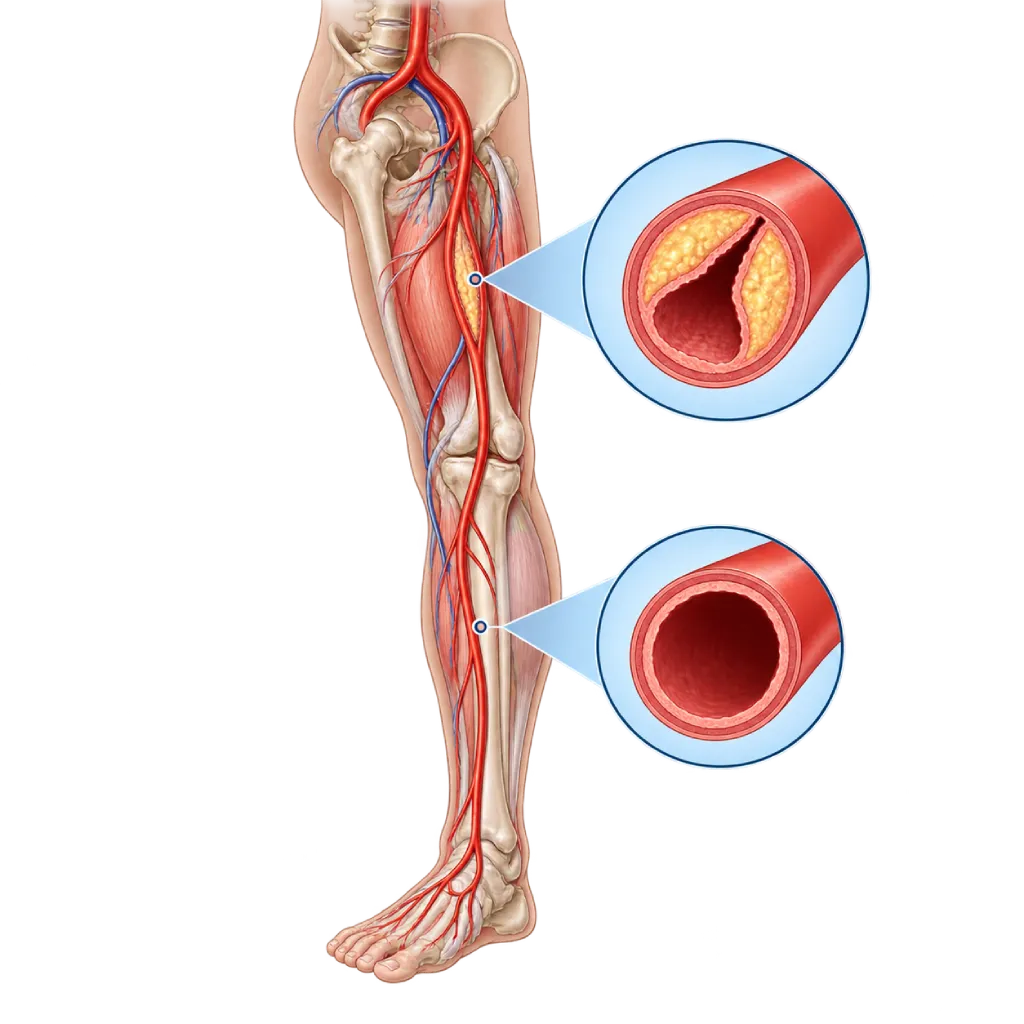
Peripheral artery disease is a narrowing of the arteries that carry blood to the legs, usually caused by atherosclerotic plaque. Its typical symptom is calf pain when walking that eases with rest, and the disease signals a higher risk of heart attack and stroke.
SourcesSigns That Need Urgent Help
- Leg pain at rest or at night that eases when the leg hangs down
- A wound on the foot or toe that does not improve within two weeks
- Toes turning bluish or black
- A foot that suddenly becomes cold, pale, and very painful
- A foot that suddenly becomes numb, weak, or hard to move
- A foot wound with pus, spreading redness, or fever
If these signs appear, go to the nearest emergency department right away or call Heart Attack Center 1500 258.
01 / Understanding the condition
About Peripheral Artery Disease
Peripheral artery disease (PAD), also called peripheral arterial disease, is a narrowing or blockage of the arteries outside the heart and brain. Arteries are the blood vessels that carry oxygen-rich blood from the heart to the whole body. The arteries usually affected are those of the legs, from the lower abdomen and pelvis, through the thigh and the back of the knee, down to the calf and foot. The main cause is atherosclerosis, a buildup of plaque made of fat, cholesterol, and calcium in the artery walls, covered on the Atherosclerosis page.
Why Your Legs Hurt
When you walk, your calf and thigh muscles need more blood. Narrowed arteries cannot increase that flow, so the muscles run short of oxygen and feel painful, crampy, or achy. After you stop for a few minutes, the muscles need less blood and the pain eases. This pattern is called intermittent claudication, covered on the Intermittent Claudication page. Many people with PAD do not feel the typical symptoms, or mistake aching legs for a sign of aging, joint pain, or a pinched nerve.
Stages of the Disease
The disease usually progresses slowly. In the early stage, the narrowing often causes no symptoms and is found only through testing. The next stage is claudication. If blood flow decreases further, pain also appears at rest, wounds on the foot are slow to heal, or the tissue of the toes turns black. This severe stage is called critical limb ischemia, covered on the Critical Limb Ischemia page, and needs prompt treatment by a vascular team. A different situation is a sudden blockage, for example by a blood clot carried in the bloodstream, covered on the Arterial Embolism page.
A Sign of Disease in Other Blood Vessels
The plaque that narrows the leg arteries is usually also present in the arteries of the heart, neck, and brain. For this reason, people with PAD have a higher risk of heart attack and stroke than other people their age. The 2024 ESC and 2024 ACC/AHA guidelines treat PAD care not only as a way to relieve leg pain but also as a way to protect the heart and brain.
A Disease That Can Be Controlled
Quitting smoking, regular walking exercise, and medicines for cholesterol, blood pressure, blood sugar, and preventing blood clots can extend your walking distance and lower the risk of complications. If symptoms still limit your activity or the leg is threatened, the doctor can restore blood flow through a catheter procedure or bypass surgery. A simple test such as the Ankle-Brachial Index (ABI) helps detect this disease earlier, before wounds appear.
02 / Understanding the condition
Types and Related Conditions
The following conditions belong to the Peripheral Artery Disease group. Open each one for a full explanation.
03 / Understanding the condition
Symptoms to Recognize.
Common Symptoms
- Pain, cramping, or aching in the calf, thigh, or buttock when walking
- Pain that eases after you stop walking for a few minutes
- One foot feels colder than the other
- A weak or undetectable pulse in the foot
- Pale, shiny skin on the legs, with thinning leg hair
- Toenails that grow slowly or become thick
- Scrapes or small wounds on the foot that heal slowly
- Erectile dysfunction in men when the narrowing is in the pelvic arteries
Symptoms in Older Adults
In older age, symptoms are often not typical because activity is already reduced or the pain is masked by joint, nerve, and spine problems.
- Walking more slowly or less often for no clear reason
- Legs that feel weak, heavy, or tire quickly, rather than painful
- Losing balance easily while walking
- Scrapes or wounds on the foot that go unnoticed
- The sole of the foot turns pale when raised and reddish when lowered
04 / Understanding the condition
What Causes This Condition?
- Atherosclerosis: plaque made of fat, cholesterol, and calcium that builds up in the walls of the leg arteries
- Calcification and thickening of the walls of the small arteries in the calf, often with diabetes and chronic kidney disease
- A blood clot that forms on top of plaque and worsens the narrowing
- Inflammation of the artery wall (vasculitis), including Buerger disease in young smokers
- Less common causes: artery injury, entrapment of the artery behind the knee, or past radiation therapy
05 / Understanding the condition
Who Is at Higher Risk?
Lifestyle
Smoking is a very strong risk factor, and the risk decreases gradually after quitting. Lack of physical activity, a diet high in saturated fat, and excess body weight also speed up plaque formation.
Medical
Diabetes, high blood pressure, high LDL cholesterol, and chronic kidney disease. Coronary artery disease or a history of stroke also signals plaque in other arteries.
Age
The risk rises gradually after age 50 and is higher still after 65. In people with diabetes who smoke, the disease can appear at a younger age.
Genetic
A family history of heart or blood vessel disease at a young age, inherited high cholesterol, and high lipoprotein(a) levels increase susceptibility.
Other
Chronic inflammatory diseases such as rheumatoid arthritis and lupus, as well as a history of radiation therapy to the pelvic area, are associated with a higher risk.
Groups at Higher Risk
- Smokers and Former Smokers: Substances in cigarettes damage the inner lining of the arteries. The risk drops after quitting, but leg symptoms still need to be checked.
- People with Diabetes: Diabetes speeds up plaque buildup and often affects the calf arteries. Nerve damage can mask pain, so a foot wound may be the first sign.
- Older Adults: At age 65 and older, the doctor may recommend an ABI test, especially if there are risk factors or symptoms when walking.
- People with Coronary Artery Disease or Stroke: Plaque in one area of the arteries is often accompanied by plaque in other areas, so blood flow to the legs also needs to be assessed.
- People with Chronic Kidney Disease: Artery calcification is more common and ABI results can appear falsely normal, so a toe pressure test is sometimes needed.
06 / Understanding the condition
How Is It Diagnosed?
Diagnosis starts with questions about your symptoms when walking, the distance you can walk before pain appears, smoking habits, and any history of diabetes, blood pressure problems, and cholesterol problems. The doctor then feels the pulses in the groin, behind the knee, and in the foot, and checks the skin color, the nails, and any wounds.
The first test recommended by guidelines is the Ankle-Brachial Index (ABI), a comparison of blood pressure at the ankle and in the arm. A value of 0.90 or lower supports the diagnosis. If the arteries are stiff because of diabetes or kidney disease, the ABI can look normal or be above 1.40, so the doctor uses the Toe-Brachial Index (TBI). If the resting ABI is normal but the symptoms are typical, the ABI can be measured again after walking exercise.
Imaging such as duplex ultrasound, CT angiography, or MR angiography is used to map where the narrowing is, especially when a procedure to open the artery is being considered. Catheter angiography is usually done together with the procedure. Blood tests check cholesterol, blood sugar, and kidney function to plan prevention.
Physical Examination
Questions about symptoms when walking and checking the pulses in the groin, behind the knee, and in the foot, along with an examination of the skin, nails, and any wounds.
Ankle-Brachial Index (ABI) Test
Compares blood pressure at the ankle and in the arm. A value of 0.90 or lower supports the diagnosis; the test can be repeated after walking exercise.
Toe-Brachial Index (TBI) Test
Used when the leg arteries are stiff because of diabetes or kidney disease, making ABI results less reliable.
Duplex Ultrasound
An ultrasound without radiation or needles that shows where the narrowing is and how fast blood flows in the leg arteries.
Peripheral CT Angiography
Maps the arteries from the abdomen to the feet using CT and contrast dye, especially before a procedure to open the artery.
Peripheral Angiography
An examination of the arteries using a catheter and contrast dye, usually done together with angioplasty or before bypass surgery.
Laboratory Tests
Blood tests for cholesterol, blood sugar or HbA1c, and kidney function to assess risk factors and plan treatment.
07 / Understanding the condition
Treatment Options.
Treatment is decided by a doctor after an assessment. The categories below can help you follow the conversation with your doctor.
Quitting Smoking
A step with a large impact on the course of the disease. Your doctor can help with counseling and medicines that support quitting.
Structured Walking Exercise
Walk until the pain is moderate, rest until it eases, then walk again, for about 30 to 60 minutes, at least three times a week for 12 weeks or longer. A supervised program gives better results.
Medicines to Protect the Blood Vessels
Cholesterol-lowering statins and antiplatelet medicines. In some patients, the doctor adds an anticoagulant. The type and dose are determined by the doctor.
Blood Pressure and Blood Sugar Control
Blood pressure and diabetes are controlled according to the targets set by your doctor to protect the leg arteries, heart, and kidneys.
Endovascular Revascularization
Balloon angioplasty, stent placement, or atherectomy through a catheter, considered when symptoms still limit you after about three months of therapy or when the leg is threatened.
Bypass Surgery
Creates a new route around the blockage using one of your own veins or a synthetic tube, mainly for long blockages. Covered on the Peripheral Bypass Surgery page.
Foot Care
Checking your feet every day, wearing well-fitting footwear, and treating scrapes early to prevent wounds and infection.
08 / Understanding the condition
Complications to Watch For.
Critical Limb Ischemia
Greatly reduced blood flow causes pain at rest, wounds that are hard to heal, or dead tissue. Covered on the Critical Limb Ischemia page.
Foot Wounds and Infection
A small scrape can become an open wound that heals slowly and gets infected easily, especially in people with diabetes.
Gangrene and Amputation
Tissue that lacks blood for a long time can die and turn black. If it cannot be saved, part of the leg or foot may need to be removed.
Heart Attack
Plaque in the coronary arteries often accompanies peripheral artery disease. Covered on the Myocardial Infarction / Heart Attack page.
Stroke
Narrowing of the neck and brain arteries is found more often in people with peripheral artery disease. Covered on the Stroke page.
Sudden Blockage in the Leg
A clot can suddenly close an already narrowed artery, so the leg suddenly becomes cold, pale, and painful. This needs treatment in the emergency room.
Reduced Walking Ability
Repeated pain reduces activity, weakens the muscles, and lowers independence in daily activities.
09 / Understanding the condition
What Can You Do?
- Quit smoking and avoid other people's cigarette smoke.
- Be physically active for at least 150 minutes per week, for example by walking briskly.
- Choose a diet rich in vegetables, fruit, nuts, fish, and whole grains, and limit saturated fat and salt.
- Control your blood pressure, blood sugar, and cholesterol according to the targets set by your doctor.
- Take your medicines regularly and do not stop them without consulting your doctor.
- If you have diabetes, check your feet every day and wear well-fitting footwear.
- Ask about an ABI test if you are 65 or older or have risk factors.
10 / Understanding the condition
When Should You See a Doctor?
Make an appointment with a doctor if you have pain, cramping, or aching in your legs when walking that eases after rest, or if you have risk factors and want the blood vessels in your legs checked. Go to the emergency room right away if your leg suddenly becomes cold, pale, numb, or very painful.
- Recurring leg pain when walking or climbing stairs
- A leg that feels cold, looks pale, or has a weak pulse
- A wound on the foot or toe that does not improve within two weeks
- Leg pain at rest or at night
- Toes that turn bluish or black
- You smoke, have diabetes, or are 65 or older
Don't Wait in an Emergency.
If symptoms are severe or come on suddenly, go to the nearest emergency department right away or call Heart Attack Center 1500 258, rather than waiting for an appointment.
11 / Common questions
Questions You May Have.
Frequently asked questions about peripheral artery disease.
Does leg pain when walking always mean peripheral artery disease?
Not always. Leg pain when walking can also come from the joints, the nerves, narrowing of the spinal canal, or the veins. Pain from the spinal nerves usually eases only when you sit down or bend forward, while pain from the arteries eases just by standing still. A quick ABI test, done without needles, helps the doctor tell them apart.
What do the ABI numbers mean?
The ABI compares blood pressure at the ankle with blood pressure in the arm. A value of 1.00 to 1.40 is generally normal, 0.91 to 0.99 is considered borderline, and 0.90 or lower supports peripheral artery disease. A value above 1.40 indicates stiff arteries, so other tests are needed. The doctor always interprets this number together with your symptoms and physical examination findings.
Can peripheral artery disease be cured?
Plaque that has already formed usually does not disappear completely, but the disease can be controlled. Quitting smoking, regular walking exercise, and medicines taken routinely can extend your walking distance, slow the narrowing, and lower the risk of heart attack, stroke, and foot wounds. Regular checkups help the doctor adjust treatment over time.
Will I definitely need a stent or surgery?
Not always. For claudication, the first steps are structured walking exercise, quitting smoking, and medicines. A procedure to open the artery is considered if symptoms still interfere with activity after about three months of therapy, or if the leg is threatened because of pain at rest and wounds. A stent or bypass does not replace medicines and lifestyle changes.
Why does the doctor also check my heart when the problem is in my leg?
The plaque that narrows the leg arteries is rarely found in just one place. Many people with peripheral artery disease also have narrowing in the arteries of the heart, neck, or brain, even if it causes no symptoms yet. By assessing the heart and risk factors as a whole, the doctor can give treatment that protects the legs while also lowering the risk of heart attack and stroke.
Can I keep walking even though my leg hurts?
Yes, and it is actually recommended once the doctor has confirmed the diagnosis. Walking until the pain is moderate, then resting until it eases and walking again, is the core of the exercise that has been shown to increase walking distance. However, if you have a wound on your foot or pain already appears at rest, ask your doctor first which type of exercise is safe for you.
Sources and Medical Review
Translated from the Indonesian edition medically reviewed by dr. Emanoel Oepangat, Sp.JP(K).
Sources as cited in the Indonesian edition.
- Mazzolai L, Teixido-Tura G, Lanzi S, Boc V, Bossone E, Brodmann M, et al. 2024 ESC Guidelines for the management of peripheral arterial and aortic diseases. Eur Heart J. 2024;45(36):3538-700.
- Gornik HL, Aronow HD, Goodney PP, Arya S, Brewster LP, Byrd L, et al. 2024 ACC/AHA/AACVPR/APMA/ABC/SCAI/SVM/SVN/SVS/SIR/VESS Guideline for the Management of Lower Extremity Peripheral Artery Disease: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation. 2024;149(24):e1313-410.
- Nordanstig J, Behrendt CA, Baumgartner I, Belch J, Back M, Fitridge R, et al. European Society for Vascular Surgery (ESVS) 2024 Clinical Practice Guidelines on the Management of Asymptomatic Lower Limb Peripheral Arterial Disease and Intermittent Claudication. Eur J Vasc Endovasc Surg. 2024;67(1):9-96.
- Conte MS, Bradbury AW, Kolh P, White JV, Dick F, Fitridge R, et al. Global vascular guidelines on the management of chronic limb-threatening ischemia. J Vasc Surg. 2019;69(6S):3S-125S.e40.
- Song P, Rudan D, Zhu Y, Fowkes FJI, Rahimi K, Fowkes FGR, et al. Global, regional, and national prevalence and risk factors for peripheral artery disease in 2015: an updated systematic review and analysis. Lancet Glob Health. 2019;7(8):e1020-30.
- Aday AW, Matsushita K. Epidemiology of Peripheral Artery Disease and Polyvascular Disease. Circ Res. 2021;128(12):1818-32.
Doctors Who Treat This Condition

dr. Suko Adiarto, Sp.JP(K), Ph.D.
Interventional Cardiology
Vascular Diagnostic and Therapeutic Center +1 center
Clinical focusCoronary Intervention · Peripheral Vascular Intervention
View Profile
dr. Emanoel Oepangat, Sp.JP(K)
Interventional Cardiology
Vascular Diagnostic and Therapeutic Center +1 center
Clinical focusCoronary Intervention · Peripheral Vascular Intervention
View Profile
Dr. med. dr. Denio A. Ridjab, Sp.JP(K)
Interventional Cardiology
Coronary Intervention Procedures +2 centers
Clinical focusInterventional Cardiology · Coronary Artery Disease
View Profile